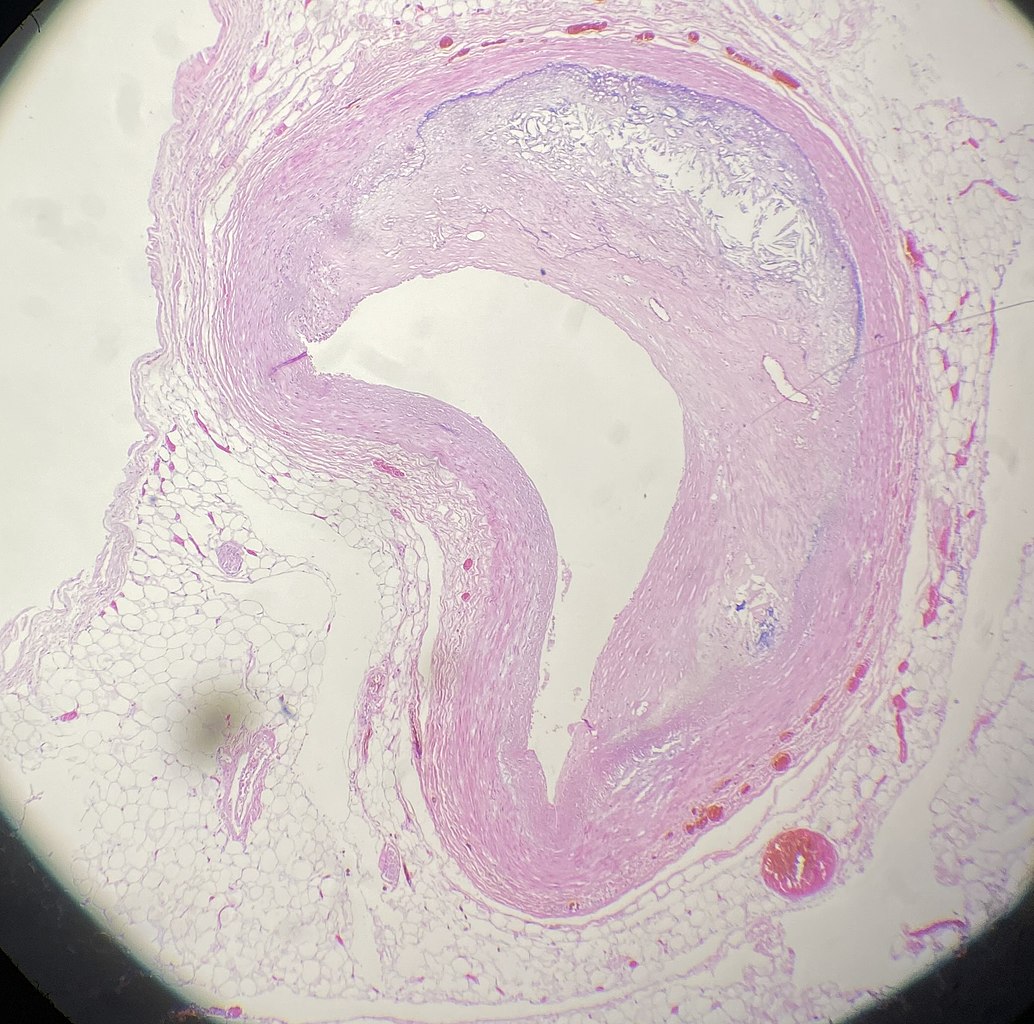
A Science Bulletin perspective says computational pathology tools must be interpretable, validated in real clinics and built to support, not replace, pathologists.
When a patient has a biopsy, a pathologist examines thin slices of the tissue under a microscope to decide whether cancer is present, what kind it is and how aggressive it appears. Those judgments shape nearly every decision that follows, from surgery to chemotherapy to targeted drugs.
Artificial intelligence has shown great promise in analyzing such tissue, often matching specialists on specific tasks in research studies. But according to a new perspective article in Science Bulletin, accuracy alone is not enough. For AI to help patients, the authors argue, it must work safely, transparently and practically inside real clinical settings.
A field under pressure
Pathology is central to cancer diagnosis and treatment, and the demands on it are growing. Hospitals face rising numbers of cases, increasingly complex biomarker testing and pressure to deliver results faster.
Many countries also face shortages of pathologists, with workloads growing faster than the workforce. That has fueled interest in tools that could take on some of the routine burden.
Computational pathology offers one route. As more laboratories digitize glass slides into high-resolution whole-slide images, AI systems can turn those images into quantitative data that support diagnosis, risk assessment, biomarker evaluation and treatment planning.
Digitizing slides is itself a significant change. For more than a century, pathology has relied on glass slides examined through a microscope. Scanning them creates gigapixel images that can be stored, shared with distant experts and analyzed by software, but it also requires expensive scanners, large amounts of data storage and changes in how laboratories work.
The field has already reached the clinic in a limited way. In 2021, the U.S. Food and Drug Administration authorized the first AI software for helping pathologists detect cancer in prostate biopsy images.
What a useful tool looks like
The authors describe computational pathology as moving from technical development toward clinical integration. To make that transition, they argue, tools must be interpretable, reportable and compatible with existing workflows.
In practice, that means a system should show what it measured, where the evidence came from, how reliable the result is and whether further testing is needed. A bare score or label, however accurate, gives a pathologist little basis for trusting or questioning it.
Interpretability has long been a concern with AI in medicine. Deep learning models can find patterns in images that humans cannot see, but they often cannot explain how they reached a conclusion, which makes it harder for clinicians to spot errors.
Researchers have also documented cases in which AI systems picked up on irrelevant features, such as markings on slides or differences in how laboratories stain tissue, rather than on the biology of disease. A system trained on images from one hospital may perform worse on images from another, which is one reason the authors emphasize validation in real-world settings.
Judging tools by their effect on care
The perspective also calls for a different way of evaluating AI tools. Rather than focusing only on accuracy in research datasets, systems should be validated in real-world settings and judged by their effects on care.
The measures the authors propose include turnaround time, diagnostic consistency, how well cases are prioritized, the amount of unnecessary testing, effects on clinical decisions and the cost of implementation. A tool that is highly accurate but slows a laboratory down, or that adds expense without changing decisions, may do little good.
Where AI could help first
The authors identify several near-term uses. AI could prescreen cases for biomarkers, helping decide which samples need costly confirmatory tests. It could prioritize urgent cases, provide quantitative scoring of features that pathologists now estimate by eye, assess how tumors respond to treatment and support decisions during surgery.
Biomarker testing is a particular pressure point. Many modern cancer drugs work only for tumors with specific molecular features, such as particular gene mutations or high levels of certain proteins. Testing for all of them can be slow and expensive, so a tool that could flag which tumors are likely to carry a given feature could help direct tests where they are most needed.
In each case, they argue, systems should target clear clinical tasks and remain under the supervision of pathologists.
Assistant, not replacement
The authors conclude that AI is unlikely to replace pathologists. Its main value, they suggest, may lie in turning the visual patterns of tissue into evidence that is computable, interpretable and actionable.
That view reflects a broader shift in thinking about AI in medicine, away from contests between algorithms and doctors and toward questions of how the two can work together safely and effectively.
The article is a perspective rather than a new study, and it presents no new data. The release does not name the authors or their institutions, and it contains no quotes from them.
Notes
- “Toward clinically integrated computational pathology: advancing diagnostic insight and practice transformation.” Science Bulletin, 2026. DOI: 10.1016/j.scib.2026.07.024.
- Science China Press. “Can AI become a trusted assistant for pathologists?” EurekAlert!, 31 July 2026. https://www.eurekalert.org/news-releases/1138351.


Leave a Reply